
Remote patient monitoring generates a continuous stream of cardiac data, but more data does not automatically mean better care. For cardiac patients, the real challenge is identifying which changes in weight, blood pressure, heart rate, symptoms, activity, and other physiological signals indicate meaningful deterioration before the patient’s condition becomes acute. Taction Software worked on a predictive cardiac remote patient monitoring approach designed around this problem. The solution combined connected-device data, longitudinal patient information, predictive deterioration detection, risk prioritization, clinician alerts, and escalation workflows to help care teams identify higher-risk patients earlier. The resulting cardiac cohort achieved a 22% reduction in readmissions, demonstrating how predictive intelligence can make remote monitoring data more clinically actionable. Taction publicly documents this outcome for predictive deterioration alerts in cardiac cohorts. The project reflects the same engineering principles Taction applies to cardiac RPM platform development: reliable device ingestion, meaningful thresholds, risk prioritization, care-team workflows, adherence support, and healthcare interoperability. Project Overview Details Industry Healthcare / Cardiology Solution Predictive Cardiac RPM Primary Use Case Early Deterioration Detection Patient Population Cardiac Cohorts Key Outcome 22% Readmission Reduction Monitoring Connected Devices + Patient-Reported Data Intelligence Predictive Analytics / Risk Detection Clinical Workflow Alerts + Care-Team Escalation Interoperability EHR / FHIR / HL7 Security HIPAA-Focused Architecture The Challenge: Turning Cardiac RPM Data Into Earlier Intervention Traditional remote patient monitoring can collect thousands of measurements without clearly identifying which patients need attention first. For cardiac care teams, the challenge was turning continuous physiological information into clinically useful signals without overwhelming clinicians with unnecessary alerts. High Risk of Cardiac Readmission Heart failure and other cardiac conditions can deteriorate between scheduled encounters. Changes may begin at home days before acute symptoms lead patients back to the emergency department or hospital. Too Much Monitoring Data Connected devices continuously generate weight, blood pressure, pulse, oxygen saturation and other readings. Without effective prioritization, care teams must manually review large volumes of data to identify patients showing meaningful deterioration. Subtle Deterioration Patterns A single abnormal reading may not indicate an emergency. The more useful signal can emerge from combinations and trends across weight, blood pressure, heart rate, symptoms, medication adherence and activity over time. Alert Fatigue Static thresholds can create large numbers of alerts, many of which require no intervention. Excessive notifications increase workload and make it more difficult for clinicians to recognize genuinely high-risk patients quickly. Disconnected Clinical Workflows RPM loses value when clinicians must constantly switch between a monitoring dashboard and the EHR. Relevant alerts and patient context need to reach care teams within workflows they already use. Taction’s broader remote patient monitoring software development practice addresses these challenges through connected-device integration, clinical dashboards, patient applications, alerts, billing workflows, and EHR interoperability. The Solution: Predictive Cardiac Remote Patient Monitoring The solution was designed to move beyond simple threshold-based monitoring. Instead of treating every abnormal measurement equally, the architecture combined longitudinal data and deterioration signals to help clinicians determine which patients required closer review. Continuous Physiological Monitoring The platform could ingest cardiac-related measurements including blood pressure, weight, heart rate, oxygen saturation and connected-device data, providing care teams with longitudinal information rather than relying exclusively on measurements collected during clinic visits. Predictive Deterioration Detection Predictive analysis evaluates changes across multiple physiological and behavioral signals to identify patterns associated with deterioration, helping move the monitoring workflow from reacting to isolated abnormal values toward recognizing developing risk. Patient Risk Prioritization Patients could be organized according to changing risk rather than presented as an undifferentiated monitoring list. This helped clinical teams focus limited attention on patients whose recent data indicated greater need for review. Tiered Clinical Alerts Alerts were designed around severity and clinical relevance so every deviation did not receive identical urgency. Tiered escalation helped distinguish routine monitoring events from situations requiring faster nurse or physician intervention. Care-Team Escalation When deterioration signals crossed defined clinical criteria, the workflow supported escalation to the appropriate care-team member for review, patient outreach, care-plan adjustment or other clinically determined intervention. Taction’s AI remote patient monitoring approach similarly emphasizes reliable ingestion, signal quality, predictive intelligence, alert triage and EHR workflow integration rather than adding AI to an isolated monitoring dashboard. Cardiac Data Captured by the RPM Platform Predictive cardiac monitoring becomes more useful when clinical decisions are based on multiple longitudinal signals rather than a single device reading. The architecture can combine connected-device measurements with symptoms and patient behavior to establish a more complete picture of changing cardiac risk. Daily Weight Rapid weight gain can be clinically relevant for heart-failure patients because it may indicate fluid retention. Connected scales allow changes to be captured remotely and evaluated alongside other physiological and symptom data. Blood Pressure Connected blood pressure monitors provide systolic and diastolic measurements outside clinical settings. Longitudinal readings help care teams identify patterns that may not be visible from occasional measurements taken during office appointments. Heart Rate and Rhythm Cardiac wearables and ECG-capable devices can provide heart-rate and rhythm information. These signals add important context when monitoring patients with heart failure, hypertension, arrhythmias or recent cardiac events. Oxygen Saturation Pulse oximeter data can contribute additional context for patients whose cardiac condition affects oxygenation or who have overlapping cardiopulmonary conditions requiring closer monitoring outside traditional care settings. Patient-Reported Symptoms Symptoms such as shortness of breath, swelling, fatigue and dizziness provide context that device readings alone cannot capture. Combining reported symptoms with physiological trends can strengthen deterioration assessment. Activity and Adherence Changes in activity, medication adherence or measurement compliance may provide additional warning signals. A patient who suddenly becomes less active or stops submitting readings may require different follow-up from a stable, adherent patient. Predictive Intelligence and Early Deterioration Detection The objective was not to replace clinical judgment. Predictive intelligence was used to help clinicians find meaningful patterns inside large volumes of RPM data and direct their attention toward patients who may require intervention. Longitudinal Trend Analysis Rather than evaluating every measurement independently, the system can examine how physiological values change over time. This provides more context for distinguishing ordinary fluctuations from sustained patterns
A regional health system partnered with Taction Software to expand virtual care across multiple specialties, including dermatology. The health system operated across urban and suburban locations with more than 200 providers across 15 specialties. Dermatology was among the specialties where patients could benefit significantly from remote access, particularly for follow-ups and cases that could be evaluated through images or virtual consultations. The broader telemedicine platform ultimately completed 50,000+ virtual visits during its first year, achieved 94% patient satisfaction, reached 92% provider adoption, and reduced new-patient time to first visit from 12 days to 3.2 days across the program. For dermatology, the virtual-care model supported both real-time consultations and image-driven workflows. Taction’s broader teledermatology platform development capabilities include store-and-forward consultations, high-resolution image capture, EHR integration, clinical documentation, patient workflows and live video visits. Project Overview Details Industry Healthcare / Dermatology Solution Teledermatology + Multi-Specialty Telemedicine Organization Regional Health System Providers 200+ across 15 specialties Virtual Visits 50,000+ in Year One across the platform Patient Satisfaction 94% across the telemedicine program Provider Adoption 92% of eligible providers EHR Epic Interoperability FHIR R4 + HL7v2 Development Timeline Approximately 8 months Client Confidential The Challenge: Expanding Dermatology Access Through Virtual Care Dermatology presented a different virtual-care challenge from general telemedicine. Skin conditions are highly visual, so clinicians needed more than standard video conferencing. The workflow had to support images, clinical context, documentation and appropriate escalation to in-person care. Limited Access to Dermatologists Specialist availability can create long waits, particularly outside major healthcare centers. Virtual dermatology offered the health system a way to extend specialist access without requiring every patient to travel for an initial assessment or routine follow-up. Visual Information Was Critical Dermatologists rely heavily on visual evidence. A conventional telemedicine application designed primarily around video conversations would not adequately address dermatology workflows requiring high-quality images, lesion history and structured clinical information. Existing Clinical Workflows Could Not Be Duplicated Providers were resistant to documenting patient encounters in separate systems. The telemedicine environment therefore needed to connect with Epic so clinicians could access relevant information without creating a second disconnected documentation workflow. Virtual and In-Person Care Needed to Work Together Not every dermatology condition is suitable for remote diagnosis. The platform therefore needed to support virtual assessment while preserving a clear pathway for patients requiring physical examination, procedures, biopsy or additional testing. Patient Experience Had to Remain Simple Patients needed straightforward ways to schedule consultations, provide clinical information and participate remotely. Adding complex technical requirements for photographs, appointments or communication could reduce adoption and undermine the accessibility benefits of teledermatology. Taction approached these challenges as specialty-care workflow problems rather than simply adding dermatology to a generic video application. The Solution: A Telemedicine Platform Adapted for Dermatology The health system’s platform was built as a multi-specialty virtual-care environment rather than separate applications for every department. This provided shared infrastructure for security, scheduling, video, EHR integration and billing while allowing specialty-specific workflows to be incorporated where required. Live Dermatology Consultations WebRTC-based HD video allowed patients and providers to meet remotely, with adaptive bitrate support for varying network conditions. Video consultations were particularly useful for follow-ups and cases requiring real-time discussion between patient and dermatologist. Store-and-Forward Workflows Teledermatology can use asynchronous workflows where patients or referring clinicians submit images and clinical history for later specialist review, allowing dermatologists to evaluate appropriate cases without requiring every patient and clinician to be available simultaneously. Dermatology Image Capture High-resolution image workflows support remote dermatology by giving clinicians visual information required for assessment. Taction’s teledermatology architecture includes secure image capture, upload, compression, storage and quality checks before cases reach dermatologists. Virtual Waiting Room Patients attending live appointments could enter a virtual waiting room before their consultation. Providers received a patient queue and daily schedule, helping virtual dermatology visits fit more naturally into existing clinical operations. Secure Patient Communication Secure in-visit messaging enabled providers and patients to exchange relevant information, documents and links during consultations while keeping communication inside the healthcare platform instead of relying on unapproved consumer communication channels. Multi-Participant Consultations The platform supported sessions involving patients, providers and additional participants such as family members or interpreters, an important capability when patients required assistance understanding treatment plans or communicating effectively during remote consultations. Building Dermatology-Specific Clinical Workflows Teledermatology requires workflows designed around the visual nature of dermatologic care. Taction’s teledermatology platform development model supports asynchronous image review and live consultations while connecting patient information, clinical documentation and follow-up decisions. Structured Patient Intake Structured intake captures symptoms, lesion history, duration, previous treatment and other relevant information before specialist review. Providing this context alongside images helps dermatologists evaluate cases more efficiently than receiving unstructured photographs alone. High-Resolution Image Review Secure imaging workflows allow dermatologists to review submitted photographs and, where supported, dermoscopic images. Maintaining useful image quality is particularly important because image detail can directly affect whether a case is suitable for remote assessment. Dermatology Case Triage Cases can be organized according to clinical urgency and appropriate specialty pathways. This helps virtual dermatology function as a triage mechanism while ensuring patients requiring direct examination can be routed toward appropriate in-person follow-up. Structured Clinical Documentation Clinical findings, diagnoses and treatment plans can be captured through structured documentation rather than isolated telemedicine notes. Integration allows virtual-care information to remain part of the patient’s broader longitudinal healthcare record. Follow-Up Care Virtual follow-ups can reduce unnecessary travel for patients whose progress can be assessed remotely. Dermatologists can review treatment response, discuss symptoms and determine whether continued virtual management or an in-person appointment is appropriate. Epic EHR Integration and Dermatology Data Exchange One of the health system’s non-negotiable requirements was EHR integration. Providers did not want to document care twice or constantly switch between the virtual-care platform and Epic. Taction therefore incorporated Epic integration directly into the architecture. Patient Information Inside the Workflow Providers could access relevant patient information, including demographics, problem lists, medications, allergies and recent results, from the telemedicine interface rather than repeatedly moving between separate applications during virtual appointments. Epic FHIR Integration Open Epic FHIR
A seed-stage digital health startup partnered with Taction Software to turn a clinical mental health concept into a production-ready telemedicine platform. The founders, a clinical psychologist and a product designer, had the clinical expertise and product vision but no internal engineering team. They also had a tight investor timeline: approximately 14 weeks to demonstrate a working product capable of serving real patients. Taction Software joined as the startup’s product engineering team and delivered the initial MVP in approximately 12 weeks. The platform combined therapist matching, secure teletherapy, patient assessments, mood tracking, messaging, scheduling, payments and therapist workflows within a HIPAA-focused architecture. Over the following 18 months, the platform grew to 100,000+ registered users, 580 therapists and 210,000+ completed sessions, while maintaining a 4.7 app-store rating and zero reported HIPAA incidents. For startups building similar products, our mental health app development services cover product strategy, clinical workflows, teletherapy, security, patient engagement and post-MVP scaling. Project Overview Details Industry Digital Health / Mental Health Solution Mental Health Telemedicine Platform Engagement MVP Development + Scaling Initial MVP ~12 Weeks Registered Users 100,000+ at 18 months Therapists 580 Sessions Completed 210,000+ App Store Rating 4.7 Reported HIPAA Incidents 0 Client Confidential under NDA The Challenge: Building a Mental Health MVP Without Compromising Clinical Care The founders needed to move quickly enough to meet investor deadlines while building software capable of handling real mental health workflows and sensitive patient information. This created a different challenge from building a conventional consumer MVP. The first release had to be usable by patients and licensed therapists, secure enough for PHI, clinically credible and technically capable of supporting rapid growth. 12-Week Launch Window The startup had approximately 14 weeks before investor meetings. Taction needed to define the product, establish the architecture, design the patient experience, develop the core functionality, test it and prepare a production-ready MVP within that compressed window. HIPAA From the First Release Because licensed therapists would use the platform to provide care, protected health information was part of the product from launch. Security, access controls, encryption, auditability and vendor requirements therefore could not be deferred until a later version. Clinical Credibility The founders did not want another generic wellness application. The product needed clinically meaningful workflows, validated assessments and therapist involvement so it could support actual mental healthcare rather than simply provide self-help content. Uncertain Growth Like most early-stage products, the team could not predict adoption. The architecture therefore needed to support a small initial user base without creating a technical ceiling if thousands of patients and therapists joined after launch. Behavioral Health Privacy The roadmap included substance-use recovery functionality, introducing additional confidentiality considerations. The architecture needed to account for consent and disclosure requirements beyond basic application privacy as the behavioral health platform expanded. Taction’s experience in behavioral health software development helped frame these requirements around actual behavioral health workflows rather than adapting generic healthcare software after development. The Solution: A Focused Mental Health Telemedicine MVP Instead of attempting to deliver the founders’ entire roadmap in version one, Taction concentrated the MVP around the most important clinical journey: connecting a patient with a licensed therapist and supporting care before, during and between sessions. That decision allowed the team to deliver meaningful functionality within the 12-week MVP window. Therapist-Patient Matching Patients could connect with therapists based on factors such as specialty, therapeutic approach, availability and preferences. This made provider discovery part of the care experience instead of forcing patients to manually search through unrelated provider listings. Secure Video Teletherapy WebRTC-based video functionality enabled therapists and patients to conduct remote sessions directly through the platform. Adaptive communication capabilities helped the experience remain usable across different network conditions without requiring a separate consumer video application. Secure Patient Messaging Asynchronous messaging allowed therapists and patients to communicate between scheduled sessions. The feature extended care beyond video appointments while keeping therapy-related communication within the platform instead of relying on personal email or consumer messaging tools. Mental Health Assessments PHQ-9 and GAD-7 assessments were integrated into the product to support structured depression and anxiety screening. Longitudinal tracking allowed assessment results to become part of the ongoing care experience rather than isolated questionnaires. Mood Tracking and Journaling Patients could record daily mood information and journal between therapy sessions. These tools helped maintain engagement outside appointments while giving the platform a structured way to capture patient-reported information over time. Therapist Dashboard Therapists received a dedicated workspace for managing patient caseloads, reviewing relevant information, documenting sessions and supporting treatment planning. The interface was designed around provider workflows rather than simply exposing the patient application to clinicians. Organizations building similar products can also explore Taction’s telepsychiatry platform development capabilities for psychiatric evaluations, therapy, measurement-based care, prescribing workflows and behavioral health integrations. Mental Health Features Included in the Initial MVP The MVP needed enough functionality to test the complete care model with actual users without becoming overloaded with secondary features. The team therefore prioritized capabilities directly connected to patient access, therapy delivery, engagement and provider operations. Appointment Scheduling Patients could schedule therapy appointments based on provider availability. Automated reminders supported attendance while giving therapists a structured way to manage upcoming sessions within the same environment used for patient communication and care delivery. Treatment Planning The therapist experience supported patient caseload management, session notes and treatment planning. Keeping these workflows connected to teletherapy reduced the need for providers to manage separate tools for appointments, patient information and ongoing care. Patient Engagement Daily mood check-ins, journaling and between-session communication gave patients reasons to engage with the platform outside scheduled appointments, turning the product into an ongoing mental health experience rather than a video-call application. Payment Processing Payment functionality supported session fees and subscription-oriented models. Integrating payments into the platform reduced friction between appointment scheduling, therapy delivery and payment while giving the startup flexibility to test different commercial models. Automated Reminders Appointment notifications and engagement prompts helped patients remember upcoming sessions and continue participating between appointments. These workflows later expanded into broader push-notification sequences for check-ins, therapeutic exercises and

Scaling Virtual Care Without Compromising Security, Clinical Workflows, or Patient Experience Taction Software helped engineer a secure, scalable telemedicine platform designed to support a growing healthcare network serving more than 500,000 patients. The platform brought virtual consultations, appointment scheduling, patient onboarding, clinical documentation, secure communication, e-prescribing workflows, and healthcare system integrations into a unified digital care experience. The challenge was not simply adding video calls. The platform needed to handle Protected Health Information (PHI), support different clinical workflows, integrate with existing healthcare systems, maintain reliable performance as patient volume increased, and give providers a virtual care workflow they could actually use. The result was a healthcare-focused telemedicine architecture built around HIPAA safeguards, interoperability, scalability, and clinical usability. Industry: Healthcare / Digital HealthSolution: Custom Telemedicine PlatformScale: 500K+ Patient PopulationCompliance: HIPAA / HITECHIntegrations: EHR/EMR, FHIR, HL7, e-Prescribing, PaymentsPlatforms: Web + Mobile Client Overview The client needed a centralized virtual-care platform capable of supporting a large and growing patient population. Patients needed a simple way to find providers, schedule appointments, complete intake information, join virtual consultations, communicate securely, receive prescriptions, and access post-visit information. Providers needed something different. They needed patient information available within their normal clinical workflow without repeatedly moving between the telemedicine application and other healthcare systems. Administrative teams also required visibility into appointments, provider availability, patient activity, operational performance, access permissions, and audit events. As adoption increased, the existing approach could no longer provide the scalability, integration, security, and operational control required for a patient population exceeding 500,000. The Challenge Building Telemedicine for Healthcare Scale A telemedicine application may appear simple from the patient’s perspective. Behind a single virtual appointment, however, are multiple systems responsible for identity, scheduling, clinical data, video communication, documentation, prescriptions, billing, notifications, and security. The client needed these components to operate as one connected workflow. HIPAA-Compliant Handling of PHI Patient demographics, medical information, consultation data, messages, documents, and other PHI had to remain protected throughout the application lifecycle. Security controls therefore needed to extend beyond the database to authentication, APIs, infrastructure, integrations, logging, user permissions, and third-party services. Growing Patient Volume The platform had to support a patient population of more than 500,000 without creating performance bottlenecks as adoption increased. The architecture needed to accommodate spikes in appointment scheduling, concurrent virtual consultations, notifications, data requests, and provider activity. Fragmented Clinical Workflows Providers could not be expected to maintain separate workflows for virtual and in-person care. Patient information needed to move between the telemedicine platform and existing clinical systems while minimizing duplicate entry. Reliable Virtual Consultations Video quality had to remain usable across different devices, browsers, networks, and bandwidth conditions. The platform also needed virtual waiting rooms, secure messaging, appointment status management, and mechanisms for handling interrupted connections. Multiple User Roles Patients, physicians, nurses, administrators, support staff, and other authorized users required different levels of system access. A single permission model would not provide adequate security or usability. Interoperability The telemedicine platform could not become another healthcare data silo. Its architecture needed to support standards such as HL7 and FHIR so clinical information could be exchanged with EHRs and other healthcare applications. What Taction Software Built Taction Software designed and developed a custom telemedicine ecosystem covering the complete virtual-care journey. Rather than treating video conferencing as the product, the engineering team designed the system around the workflows occurring before, during, and after each virtual encounter. Patient Application Patients received a streamlined digital experience for managing their virtual care. Core capabilities included: The interface was designed to reduce unnecessary steps between scheduling an appointment and connecting with a healthcare professional. Provider Portal The provider experience was designed around clinical efficiency. Providers could manage their virtual appointments and access relevant patient information without turning the telemedicine system into another disconnected administrative application. The provider portal included: Where integrations were available, relevant information could be exchanged with existing clinical systems rather than manually entered twice. Secure Video Consultation Reliable real-time communication formed one part of the platform rather than the entire platform. The video consultation workflow supported secure provider-patient communication along with the operational capabilities needed around the call. Features included: HD video and audio Adaptive communication capabilities helped maintain consultations across varying network conditions. Virtual waiting room Patients could check in before their appointment while providers managed their upcoming consultation queue. Secure messaging Patients and providers could communicate securely around the consultation workflow. Document sharing Relevant clinical information and documents could be exchanged within authorized workflows. Multi-device access Patients could access virtual care through supported web and mobile experiences. Connection management The application was designed to handle temporary connectivity problems without forcing users to restart the entire appointment process. EHR and Healthcare System Integration One of the most important requirements was preventing the telemedicine platform from becoming an isolated system. Taction Software designed the integration layer around healthcare interoperability standards. The architecture could support connections using: HL7 v2 HL7 interfaces support the exchange of clinical and administrative information with existing hospital and healthcare systems. FHIR APIs FHIR-based APIs enable modern exchange of patient demographics, appointments, encounters, medications, observations, clinical documents, and other supported resources. Integration Engine Integration engines such as Mirth Connect can be used to transform, route, validate, and monitor messages between the telemedicine platform and external healthcare applications. EHR/EMR Integration The architecture supports integration strategies for platforms such as Epic, Oracle Health/Cerner, athenahealth, NextGen, and other healthcare systems where appropriate interfaces are available. Learn more about Taction Software’s EHR integration services. HIPAA Compliance Built Into the Architecture HIPAA requirements were treated as architecture requirements rather than a checklist applied after development. Taction Software’s broader HIPAA development approach includes encryption, access controls, authentication, audit logging, HIPAA-eligible cloud infrastructure, and appropriate Business Associate Agreements. TactionSoft Encryption Sensitive healthcare information was protected during transmission and storage using appropriate encryption controls. This included protecting PHI moving between: Patient applicationsProvider applicationsBackend APIsDatabasesIntegration servicesExternal healthcare systems Role-Based Access Control Access was designed around user roles and responsibilities. A patient, provider, administrator, and support employee should not have identical access to healthcare information.
Remote patient monitoring generates a continuous stream of valuable cardiac data, but collecting more measurements does not automatically help clinicians identify which patients need attention first. This project focused on building a predictive cardiac RPM workflow that transforms incoming patient data into clinically useful deterioration signals and prioritized alerts. The solution combines connected-device data, predictive analytics, clinical workflow logic, and healthcare interoperability to help care teams identify meaningful changes across monitored cardiac populations without relying entirely on static threshold alerts. Building a Predictive Remote Patient Monitoring System for Cardiac Care Traditional RPM systems commonly alert clinicians when an individual measurement crosses a predefined threshold. Predictive RPM goes further by evaluating trends and multiple patient signals over time. Taction Software’s remote patient monitoring developers build these workflows around device integration, time-series data, predictive deterioration scoring, clinician dashboards, and escalation logic. Continuous Cardiac Data Collection Predictive monitoring starts with reliable longitudinal patient data. The architecture can ingest measurements such as blood pressure, heart rate, weight, ECG-related signals, activity, symptoms, and other connected-device observations, creating a continuous patient timeline that can be evaluated for meaningful changes rather than isolated measurements. Predictive Deterioration Analysis Machine-learning models can evaluate combinations of physiological signals and longitudinal trends to identify patterns associated with worsening cardiac status. Instead of waiting for one measurement to exceed a fixed threshold, predictive analysis helps surface changes across multiple variables that may indicate increasing clinical risk. AI-Driven Alert Prioritization High alert volumes can make traditional RPM difficult to manage at scale. Predictive scoring provides another layer for prioritizing incoming signals according to patient context and deterioration patterns. Taction’s healthcare AI demo gallery demonstrates this pattern through predictive cardiac RPM and AI-assisted alert prioritization workflows. FHIR-Based EHR Integration Predictive insights become more useful when they are connected to the systems clinicians already use. Using healthcare interoperability standards, RPM observations and relevant outputs can be incorporated into EHR workflows. Taction’s FHIR developers work with resources such as Observation, Device, Patient, and related clinical data structures. Cardiology-Specific AI Engineering Cardiac RPM requires more than a generic predictive model because physiological signals are longitudinal, interconnected, and clinically contextual. Taction’s cardiology AI development capabilities include predictive deterioration, ECG analysis, heart-failure monitoring, post-MI risk workflows, and AI-assisted prioritization for remote cardiac monitoring programs. Clinician Review and Escalation Workflows Predictive scores should support clinical teams rather than operate as autonomous clinical decisions. The workflow can route prioritized cases into clinician dashboards, apply defined escalation rules, preserve supporting patient measurements, and record actions so care teams can evaluate why a patient was surfaced and determine the appropriate response. The Challenge: Turning RPM Data Into Actionable Clinical Signals Remote monitoring platforms can collect thousands of measurements across a patient population. The operational challenge is deciding which changes deserve attention. Simple threshold-based monitoring can identify obvious abnormalities, but it may also produce repetitive alerts without considering the patient’s longitudinal pattern. A single measurement may not be significant on its own, while several smaller changes occurring together can potentially indicate a meaningful shift. For cardiac monitoring, the system therefore needs to evaluate patient data over time while giving clinicians enough context to understand why a case has been prioritized. The objective of predictive RPM is not simply to generate another alert. It is to help organize continuous patient data into a workflow clinicians can review and act upon. The Solution: A Predictive Cardiac Monitoring Pipeline The solution was structured as a connected healthcare data pipeline rather than a standalone machine-learning model. Connected Devices and Patient Inputs ↓ Secure RPM Data Ingestion ↓ Normalization and Validation ↓ Longitudinal Patient Data ↓ Feature Engineering ↓ Predictive Risk Analysis ↓ Risk and Alert Prioritization ↓ Clinician Dashboard ↓ Clinical Review ↓ Escalation or Intervention ↓ EHR Documentation This architecture separates data collection, prediction, clinical presentation, and clinician action. That separation is important because each layer has different technical and clinical responsibilities. From Threshold Alerts to Longitudinal Risk Traditional RPM rules typically operate on predefined limits. For example, a monitoring program may create an alert when blood pressure, heart rate, weight, or another measurement moves outside an established range. These rules remain useful, but they evaluate individual events. Predictive monitoring can add longitudinal context. The system can evaluate how measurements change across time and whether combinations of variables are moving in a direction associated with deterioration. Depending on the clinical program, inputs may include: The resulting risk signal can then complement established clinical thresholds rather than replacing them. Reducing Alert Fatigue Through Prioritization A remote monitoring platform becomes difficult to operate when every abnormal reading creates the same level of urgency. Clinical teams need prioritization. Predictive scoring can help separate routine deviations from patterns that warrant closer review. Instead of presenting clinicians with an undifferentiated queue of device alerts, the system can combine patient measurements, longitudinal changes, predefined rules, and model outputs to organize cases by urgency. Importantly, prioritization should remain explainable enough for clinicians to understand what information contributed to the alert. A useful dashboard therefore shows the underlying patient measurements and trends alongside the predictive signal. Healthcare Interoperability and FHIR RPM data should not become another isolated healthcare data silo. The integration architecture can use FHIR to exchange patient, device, and observation information with other clinical systems. Relevant resources may include: Patient — identifies the monitored patient. Device — represents the connected monitoring device. Observation — carries measurements such as blood pressure, weight, heart rate, and oxygen saturation. Encounter — provides relevant clinical context when applicable. CarePlan — can represent elements of an ongoing monitoring program where supported by the workflow. The exact implementation depends on the target EHR and available interfaces. FHIR-based integration allows the RPM platform to participate in a broader clinical ecosystem rather than requiring clinicians to manually reconcile disconnected patient information. Designing the Clinician Dashboard Predictive analytics are only useful when the output can be interpreted efficiently. The clinician-facing experience should make it possible to understand: Rather than showing only a numerical risk score, the interface should expose the supporting
Building an AI-Assisted Clinical Documentation Workflow Around Real Patient Encounters Clinical documentation should support patient care—not compete with it. For a healthcare organization operating across 12 clinics, documentation creates a difficult engineering and workflow problem. Clinicians need to capture clinically meaningful information during each encounter while keeping documentation accurate, reviewable, secure, and connected to the existing electronic health record. Taction Software worked on an ambient clinical documentation solution designed around that workflow. The system captures the clinical conversation, converts speech into text, transforms the encounter into a structured clinical-note draft, and keeps the clinician in control of review and approval before information becomes part of the clinical record. Rather than treating generative AI as a standalone transcription tool, the architecture was designed around the complete documentation lifecycle: encounter capture, transcription, structured note generation, clinician review, EHR integration, security, and auditability. Project at a Glance Organization: Multi-location healthcare groupScale: 12 clinicsIndustry: Healthcare / Ambulatory CareSolution: Ambient Clinical DocumentationCore Capabilities: Clinical speech capture, medical transcription, AI-generated structured notes, clinician review, EHR workflow integration, audit loggingEngineering Focus: Healthcare AI, clinical NLP, LLM integration, interoperability, HIPAA-oriented architecture The Challenge: Documentation Was Part of the Clinical Workflow, Not a Separate AI Problem Ambient documentation can appear straightforward at the prototype stage. Record an encounter. Convert the recording to text. Send the transcript to a large language model. Generate a SOAP note. That approach may produce an impressive demonstration, but a production clinical workflow requires considerably more engineering. A usable system needs to understand who is speaking, handle medical terminology, preserve encounter context, generate the correct note structure, control PHI throughout the processing pipeline, allow clinicians to review AI-generated content, and return approved documentation to the systems clinicians already use. For a group operating across 12 clinics, consistency also matters. Different providers may document differently. Visit types vary. Specialty terminology changes. Templates can differ between workflows. The solution therefore had to support clinical variation without turning every provider preference into a separate application. The objective was not simply to automate transcription. It was to create a documentation workflow that could assist clinicians while preserving human review and fitting into existing clinical operations. The Solution An Ambient Documentation Pipeline Built Around the Encounter Taction approached the project as an end-to-end clinical documentation system rather than an isolated generative AI feature. The workflow was structured around several connected layers. 1. Ambient Encounter Capture The documentation workflow begins during the clinician-patient encounter. Audio capture provides the source material from which the documentation pipeline operates. The architecture must therefore treat the recording as sensitive clinical information from the moment it enters the system. Instead of requiring the clinician to dictate a separate note after the visit, ambient capture allows the documentation process to begin from the natural clinical conversation. 2. Medical Speech-to-Text Processing Clinical conversations contain terminology that general speech-recognition systems frequently struggle with. Medication names, abbreviations, diagnoses, anatomical terminology, numbers, measurements, and specialty-specific vocabulary all affect transcription quality. The transcription layer converts the encounter audio into machine-readable text that can be processed by the documentation engine. Speaker separation is also important because a clinical note must distinguish between information reported by the patient and observations, questions, or decisions made by the clinician. 3. Clinical Context and Transcript Processing A raw transcript is not a clinical note. Conversation includes greetings, repetition, clarification, incomplete sentences, unrelated discussion, and information that belongs in different areas of the medical record. The processing layer prepares encounter information for structured documentation while preserving the clinical context needed by the generation system. This creates a cleaner boundary between transcription and clinical-note generation. 4. AI-Generated Structured Clinical Notes The processed encounter is transformed into a structured draft rather than a generic conversation summary. Depending on the clinical workflow, the output can follow formats such as: Prompting and generation logic can be tuned around the organization’s preferred documentation structure. The goal is not simply shorter text. The goal is to produce a useful clinical draft that reflects the encounter while fitting the format clinicians expect to review. Human Review Remained a Core Part of the Architecture Clinical documentation is part of the legal medical record. For that reason, the workflow was designed around AI-assisted documentation rather than autonomous documentation. The generated note is presented as a draft. The clinician remains responsible for reviewing the output, correcting or modifying information where necessary, and approving the final documentation. This human-in-the-loop architecture creates an important separation between AI generation and clinical authorization. The AI prepares the documentation. The clinician decides what becomes part of the record. EHR Integration: Bringing the Output Back Into Clinical Workflow One of the biggest differences between an AI prototype and production healthcare software is what happens after the model produces an answer. A standalone AI interface can create another workflow clinicians need to manage. The documentation therefore needs a defined path back into the clinical environment. Taction’s broader ambient-documentation architecture supports standards-based EHR integration patterns including FHIR resources and clinical encounter context. The integration layer can associate documentation with the correct patient and encounter and support controlled write-back into the clinical workflow. This reduces the need for clinicians to manually move generated documentation between systems. Healthcare AI Architecture A production ambient documentation system can be viewed as a controlled pipeline: Clinical Encounter ↓ Secure Audio Capture ↓ Medical Speech Recognition ↓ Speaker Identification / Diarization ↓ Transcript Processing ↓ Clinical Context Layer ↓ LLM-Based Note Generation ↓ Structured Clinical Note ↓ Clinician Review and Editing ↓ Clinician Approval ↓ EHR Documentation Workflow ↓ Audit and Monitoring Each stage has different clinical, security, integration, and reliability requirements. Treating them as separate architectural layers also makes the system easier to evaluate and improve. Designing for HIPAA and PHI Handling Ambient documentation systems process some of the most sensitive information in healthcare: actual conversations between patients and clinicians. Security and privacy therefore cannot be added after the AI functionality has been completed. The architecture should define how PHI moves through every component involved in the workflow. That includes:
What an ED Triage Copilot Does, and What It Must Never Do An emergency department triage copilot assists the triage nurse by retrieving relevant institutional protocol guidance, drafting a suggested acuity level, and surfacing time-critical patterns that warrant immediate escalation. What it must never do is decide. Acuity assignment remains a clinical judgement made by a licensed clinician, and every architectural decision in a defensible deployment follows from that boundary. Systems that blur it fail clinical safety review, and rightly so. The engineering challenge is building something genuinely useful inside that constraint rather than something impressive outside it. Protocol Retrieval Under Time Pressure The copilot surfaces the relevant section of the hospital’s own triage protocol for the presentation in front of the nurse, with the source text visible rather than summarized away. Draft Acuity With Reasoning Shown A suggested level accompanied by the specific findings that drove it. A number without reasoning cannot be evaluated by the clinician and should not be displayed. Pattern Surfacing on Time-Critical Presentations Suspected stroke, myocardial infarction, sepsis, and occult trauma warrant immediate flagging. These paths are deterministic rules, not model inference. Documentation Support Structured capture of presenting complaint, vitals, and triage rationale reduces keyboard time during the encounter, which is often the benefit clinicians value most. What Stays With the Clinician Final acuity, disposition, and escalation authority remain entirely with the nurse or provider in triage. The copilot has no write authority over acuity fields. Where the Deeper Engineering Detail Sits For architecture-level treatment of retrieval design, guardrails, and latency engineering, see our AI triage copilot build guide. Why Under-Triage Is the Only Error That Really Matters Aggregate accuracy is the wrong metric for triage, and any evaluation reporting it as a headline has misunderstood the problem. Over-triage consumes beds, staff attention, and money. Under-triage on a presentation that deteriorates causes patient harm. These are not symmetrical errors and cannot be averaged into a single figure. A model with strong overall concordance that misses one stroke presentation in a hundred is unsafe regardless of how the summary statistic reads. Evaluation therefore has to be stratified by presentation type and weighted toward false-negative behavior on emergent categories. Stratify Evaluation by Presentation Performance on chest pain, altered mental status, abdominal pain, and minor injury are separate questions. Combined figures conceal exactly the failures that matter clinically. Set False-Negative Tolerance Explicitly For emergent presentations the tolerance approaches zero, which is why those categories are handled by deterministic routing rather than by model judgement in any responsible design. Consistency Is the Honest Objective Published research has found substantial agreement between language model triage and clinician triage, but agreement is not superiority. The defensible aim is reducing variance between staff, not replacing judgement. Measure Concordance, Not Correctness Without a gold standard at the moment of triage, the practical measure is agreement with senior clinician review on divergent cases. Design the data capture for that from the start. Watch Automation Bias A confident suggestion shifts human judgement even where the human retains authority. Interfaces that display the model’s answer before the nurse forms their own introduce measurable anchoring. Ongoing Monitoring Is Not Optional Model behavior drifts as presentation patterns, documentation habits, and protocols change. Governance for this sits in our healthcare AI governance framework. Architecture of a Production Triage Copilot The architecture is constrained by three hard requirements: sub-second response, grounding in the hospital’s current protocols, and a complete audit trail of every suggestion and every clinician response to it. Those requirements rule out several common patterns. General-purpose model calls without retrieval produce plausible guidance that does not match institutional policy. Retrieval over a stale document set produces citations to superseded protocols. Systems without per-suggestion logging cannot support safety review, which means they cannot be defended after an adverse event. Structured Ingestion of Presentation Data Chief complaint, vitals, arrival mode, age, and relevant history arrive as structured inputs. Free-text-only input degrades both retrieval quality and reproducibility. Retrieval Over Versioned Institutional Protocols The corpus is the hospital’s own triage policy, indexed with version control so retrieved guidance can be traced to the document revision in force at that time. Deterministic Guardrails Ahead of Inference Red-flag combinations route immediately and unconditionally. The model never gets the opportunity to reason its way past a time-critical presentation. Latency Budget as a Design Constraint Triage does not wait. Retrieval, inference, and rendering must complete inside a budget measured in hundreds of milliseconds, which shapes model and hosting choices. In-Workflow Integration The copilot lives inside the EHR triage workflow and the worklist priority logic. A separate application, however capable, is not used under pressure and therefore delivers nothing. Per-Inference Audit Logging Every suggestion, its inputs, the retrieved sources, the clinician’s decision, and any override reason are logged. Our healthcare AI audit logging page covers trail design. Designing Human-in-the-Loop So It Actually Holds Nearly every vendor claims human-in-the-loop. Far fewer have engineered it. The phrase describes an outcome, and the outcome depends on interface sequencing, override capture, and review process rather than on policy language. If the clinician sees the model’s acuity before recording their own, independence is compromised whatever the documentation says. If overrides are possible but never reviewed, the most valuable safety signal in the system is discarded. These are build decisions, made early, and expensive to retrofit. Capture Clinician Judgement First Record the nurse’s own assessment before displaying the suggestion. This preserves independence and produces genuine concordance data rather than confirmation of anchoring. Treat Overrides as Primary Data Log override reasons with structured codes and review them on a defined cadence. A rising override rate on a presentation type is an early signal of model degradation. Ground Every Suggestion in Retrievable Text Show the protocol passage behind the recommendation. Verifiable output invites appropriate scrutiny; unsourced output produces either over-trust or blanket dismissal. Make the Record Reflect What Happened Document that a suggestion was offered and what the clinician did with it. This matters for audit, for safety review, and for any retrospective question
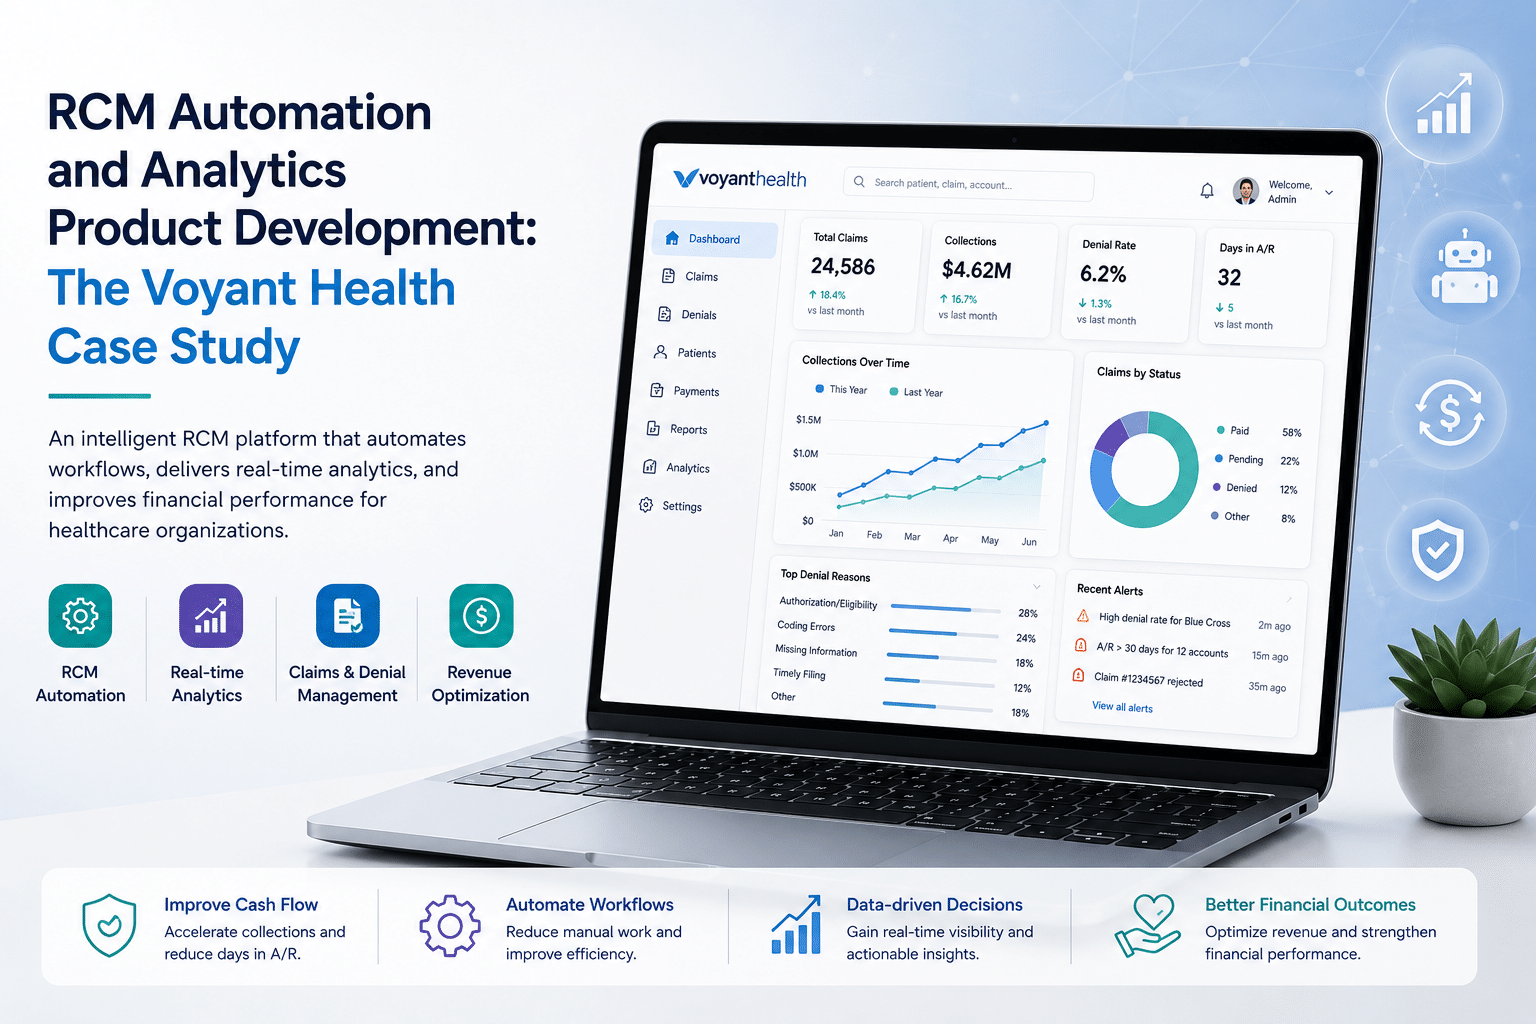
Taction Software built and launched a new product for Voyant Health, a Santa Monica-based group of RCM consultants delivering technology solutions that enhance revenue cycles for healthcare providers and medical billing companies. Voyant’s technology practice covers automation, workflow, data, and advanced analytics, with automation applied to repetitive revenue cycle tasks including data extraction, eligibility and benefits checks, payment posting, and records retrieval. The product launched on schedule. Quick Results Outcome Detail Delivery Launched on time, against a go-to-market date rather than an internal deadline Product scope Automation and analytics supporting revenue cycle operations Automation targets Data extraction, eligibility and benefits verification, payment posting, records retrieval System compatibility Works across the major EHR and practice management systems Voyant’s clients run Client outcome Product supports Voyant’s evolving business strategy and market position Client audience served Medical billing and RCM companies, provider executives and owners, private equity and institutional investors “Taction has proved their expertise in timely project delivery and this helped us to a successful on-time launch. Our new product can now truly support our evolving business strategy to remain at the forefront of our sector.” Sean McSweeney, Chief Advisory Officer, Voyant Health Book a 30-minute build assessment Client Overview Voyant Health is a group of RCM consultants delivering growth and technology solutions that enhance revenue cycles and optimize processes for healthcare providers and medical billing companies. The team combines marketing and sales professionals, data scientists, engineers, and revenue cycle leaders. The firm’s origin explains its product requirements. Voyant’s founders previously built and ran a large national medical billing company, Cobalt Health, which merged in a private-equity-backed roll-up and eventually became Coronis Health. The technology they had built to solve their own billing problems became the basis for helping other billing companies solve the same ones. Chief Advisory Officer Sean McSweeney brings that operating history plus prior roles at 4medica, Toshiba Medical, and GE Healthcare. Voyant’s work has been featured in HFMA, Medical Economics, Becker’s, and Modern Healthcare. Voyant serves three audiences: medical billing and RCM businesses, executives and owners of healthcare providers, and private equity and institutional investors. Taction Software was engaged to build the product behind Voyant’s technology solutions practice. The Challenge Revenue cycle management runs on repetitive work. Someone extracts data from a payer portal. Someone checks eligibility and benefits. Someone posts a payment. Someone requests records. Multiply that across thousands of claims and the labor cost defines the margin of the entire business. Voyant needed a product that addressed four constraints at once. Labor cost as the binding constraint. Billing companies compete on cost per claim. Every task performed by a person rather than a system is margin that competitors with better automation will take. Staffing gaps that will not close. Certain revenue cycle functions are persistently hard to staff. Automation has to fill those gaps reliably, because a program that only works when fully staffed does not solve the problem it was bought to solve. Heterogeneous client systems. Voyant’s clients run different EHR and practice management platforms. A product that only works against one system is a feature, not a business. Analytics that drive decisions, not reports. Benchmarking, KPI development, operational performance targets, and performance monitoring only matter if the underlying data is trustworthy and current. Analytics on stale or inconsistent data produces confident wrong answers. And a fifth constraint that shaped delivery more than any of the others: the launch date was a commercial commitment. Voyant is a consulting firm whose credibility rests on delivering results for clients. A product that slips does not just miss a date, it undermines the positioning the product exists to support. Our Solution An automation and analytics product built for the specific repetitive tasks that consume revenue cycle labor, designed to operate across the range of EHR and practice management systems Voyant’s clients already run. Automation handles the high-volume, low-judgment work: extracting data, verifying eligibility and benefits, posting payments, and retrieving records. The analytics layer sits on the resulting data, supporting KPI development, performance target setting, and ongoing monitoring. This is the same territory as our medical billing software development practice. Implementation and Approach Requirements from operators, not from a spec. Voyant’s team had run a national billing company. The requirements came from people who had performed the work being automated, which removes the usual discovery risk of building automation for a process nobody on the project has actually done. Automation scoped to task, not to process. Rather than attempt end-to-end process automation, individual repetitive tasks were targeted. Task-level automation deploys faster, fails more safely, and produces measurable results sooner than a process-wide rebuild. Multi-system compatibility designed in. Because client organizations run different EHR and practice management systems, the product was built to work across them rather than against a single integration target. Our healthcare integration and interoperability practice handles this class of problem. Analytics on a consolidated data layer. Benchmarking and KPI monitoring were built on the data automation produces, so metrics reflect current operations rather than periodic manual exports. Compliance treated structurally. Revenue cycle automation touches protected health information at every step. Encryption in transit and at rest, access control, and audit logging follow the standard we apply across HIPAA-compliant software development. Delivery managed to the launch date. The date was fixed and commercial. Scope was sequenced so the launch-critical path stayed protected, which is why the product shipped on time. Technology Stack Layer Requirement it had to satisfy Automation layer Scripted task automation deployable quickly against payer portals and client systems Data layer Consolidation of extracted revenue cycle data into a queryable, analytics-ready store Analytics layer KPI definition, performance target tracking, and ongoing monitoring Integration layer Compatibility across the major EHR and practice management systems in Voyant’s client base Security Encryption in transit and at rest, role-based access control, audit logging Insert the actual technologies before publishing. Every other case study in this set names its stack off the portfolio slide, and prospects evaluating a build partner read the stack table closely. I have described what
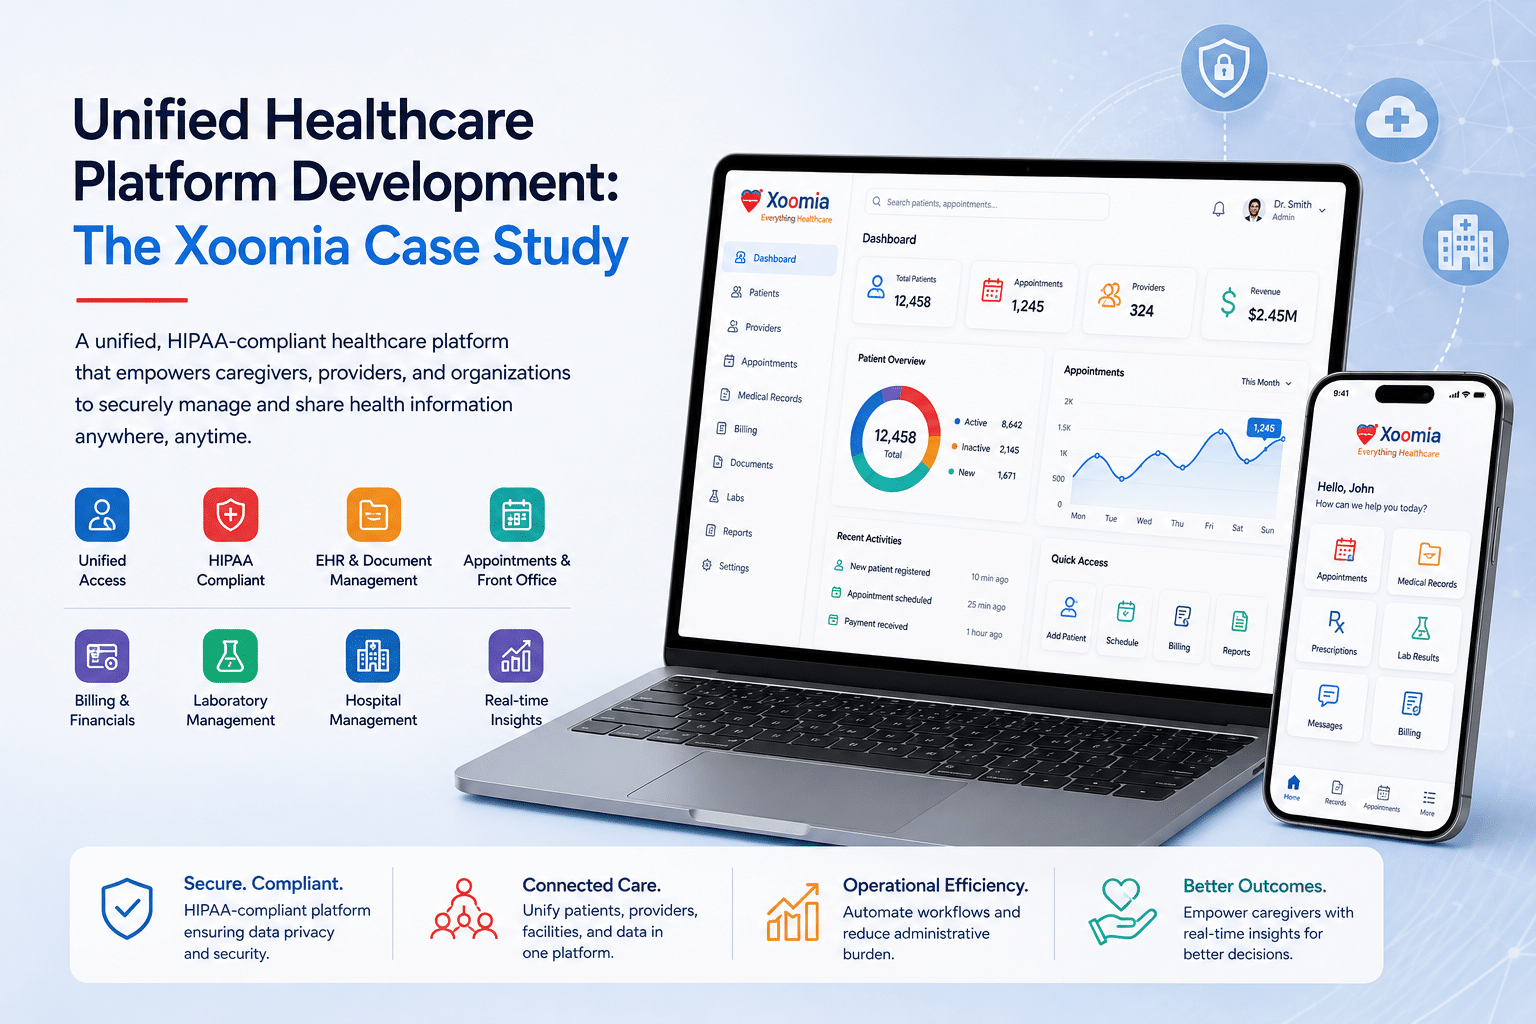
Taction Software built Xoomia, a HIPAA-compliant SaaS platform that allows caregivers, home health agencies, doctor offices, clinics, and government bodies to securely manage and share individual patient health information from anywhere. The platform provides a unified EHR spanning patients, doctors, hospitals, and laboratories, alongside reports and document management, billing and financial transaction management, front office appointment and doctor management, and hospital management. It runs on Java, React, and Mirth Connect. Quick Results Outcome Detail Participant types connected Caregivers, home health agencies, doctor offices, clinics, government bodies, plus pharmacy, facility, and insurance participants EHR scope Unified record spanning patients, doctors, hospitals, and laboratories Compliance posture HIPAA-compliant SaaS architecture, accessible anywhere, anytime Client cost model No setup fees, no hardware purchase, no in-house tech support required Modules delivered Authentication, unified EHR, reports and documents, billing, front office, hospital management Integration engine Mirth Connect for cross-system health data exchange Book a 30-minute platform assessment Client Overview Xoomia is a unified healthcare system that allows caregivers, home health agencies, doctor offices, clinics, and government bodies to securely manage and share individual patient health information. The platform is HIPAA compliant and accessible anywhere, anytime, positioned around unified electronic documentation for health providers. Facilities using Xoomia manage their patients proactively rather than reactively. The platform is delivered affordably, with no setup fees, no hardware purchase, and no requirement for in-house technical support. Taction Software built the platform, spanning the unified record layer, the participant-specific interfaces, the integration engine connecting external systems, and the administrative and financial modules underneath. The Challenge A patient in home or community care is handled by participants who do not share a system and often do not share an employer. A caregiver visits the home. A home health agency coordinates the schedule. A doctor’s office holds the clinical history. A laboratory produces results. A pharmacy dispenses. A facility admits when care escalates. An insurer adjudicates. A government body oversees eligibility and compliance. Every one of them holds part of the record, and none of them holds all of it. Xoomia needed four problems solved together. No shared record across participant types. Information moves between these parties by phone, fax, and paper. What gets lost in transit is clinical context, and the cost of losing it is duplicated tests, medication errors, and avoidable admissions. Different participants need different views. A caregiver in a home, a physician in an office, and a government reviewer need the same underlying record presented in entirely different ways, with entirely different permissions. Adoption barriers at the small end of the market. Home health agencies and small practices do not have IT budgets, server rooms, or technical staff. A platform requiring setup fees, hardware, or in-house support excludes exactly the participants the network needs most. Connection to systems already in place. Hospitals and laboratories already run their own systems. A unified platform that cannot receive from them is another silo with better branding. Our Solution One record, many participants, role-appropriate access. Xoomia holds a unified electronic health record spanning patients, doctors, hospitals, and laboratories, and exposes it through interfaces built for each participant type. Around it sit the administrative and financial modules a care operation actually runs on, plus a Mirth Connect integration layer that brings in data from external clinical systems. Delivered as SaaS, the platform requires no hardware, no setup fee, and no internal IT capability from the organizations using it. This is the architectural approach behind our unified EHR and EMR software development work. Implementation and Approach Participant and permission mapping first. We mapped every participant type and what each legitimately needs to see before designing the data model. In a platform where caregivers, clinicians, insurers, and government bodies share a record, access control is the architecture, not a settings screen. Unified record design. The record was built to hold clinical, laboratory, and encounter data from multiple sources without privileging any one participant’s format. HIPAA compliance as a structural requirement. Encryption in transit and at rest, role-based access control, and audit logging were specified before feature work, following the standard we apply across HIPAA-compliant software development. With this many parties touching one record, audit trails are not a compliance checkbox, they are how the platform stays trustworthy. Mirth Connect integration layer. Channels built to receive and transform data from hospital and laboratory systems, so external clinical data enters the unified record in usable form. Our Mirth Connect integration practice was applied directly. Role-specific interfaces on shared data. Caregiver, clinical, front office, and administrative views built on one record rather than on separate datasets per user type. Administrative and financial modules. Reports and document management, billing and transaction management, front office appointment and doctor management, and hospital management built as part of the platform rather than as adjacent tools. Zero-infrastructure SaaS delivery. Multi-tenant delivery with no setup fee, no hardware requirement, and no client-side technical support burden, removing the adoption barrier for smaller participants. Technology Stack Layer Technology Engineering rationale Backend Java Mature ecosystem for complex permission models, transactional integrity, and long-lived healthcare systems with strict access control requirements Frontend React Component model suits building distinct participant interfaces on shared data structures without duplicating the front end per user type Integration engine Mirth Connect Industry-standard healthcare interface engine for routing and transforming data from hospital and laboratory systems Delivery Multi-tenant SaaS No hardware or setup cost for participating organizations React was the right choice specifically because of the participant-type problem. Building separate interfaces for caregivers, clinicians, and administrators on shared components keeps one codebase serving many audiences. If your organization already runs a stack, we build in it. Key Features Login and signup. Authentication with role-based access separating caregiver, clinical, administrative, and oversight paths. HIPAA-compliant SaaS solution. Multi-tenant architecture with encryption in transit and at rest, access control, and audit logging, accessible anywhere, anytime. Unified EHR. A single record spanning patients, doctors, hospitals, and laboratories, so clinical history is not reassembled from separate sources at each encounter. Reports and document management. Structured storage and retrieval of
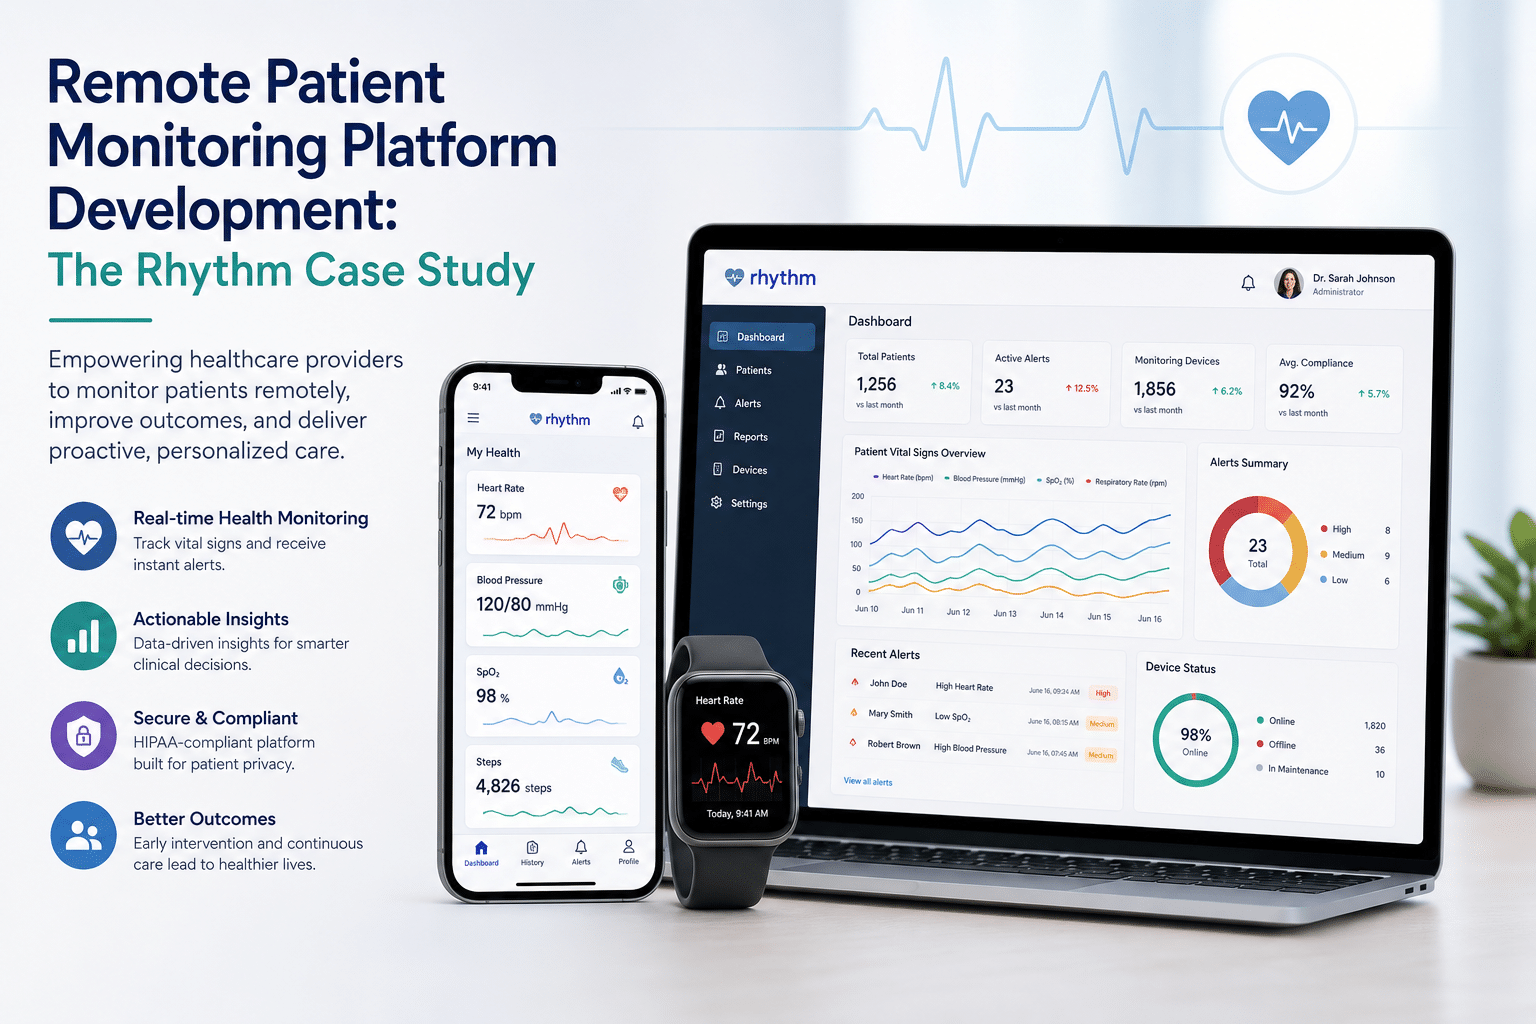
Taction Software built Rhythm’s remote patient monitoring platform, a SaaS system serving both patients and clinics across the full RPM lifecycle. It covers patient enrollment and insurance verification, patient identification and onboarding, device ordering and direct-to-patient shipping with training, device problem resolution, ongoing monitoring, real-time triaged alerts, billing guidance, and bi-directional EHR integration. The platform runs on Node.js, AngularJS, and MongoDB. Quick Results Outcome Detail Lifecycle coverage Enrollment through monitoring, alerting, and billing in one platform User groups served Patients and clinics on a single SaaS system Device logistics Ordering, direct-to-patient shipping, patient training, and problem resolution built in Alerting model Real-time alerts triaged before reaching clinical staff EHR connectivity Bi-directional integration, data flowing both ways Reimbursement support Billing expertise and guidance embedded in the workflow Book a 30-minute RPM platform assessment Client Overview Rhythm is a proven leader in remote monitoring with a track record of delivering innovative technology and unmatched service. Its remote monitoring solutions are built so clinical teams can focus on patient care rather than on program administration. Taction Software was engaged to build the SaaS platform underneath that operation, spanning the patient-facing experience, the clinic-facing monitoring and alerting interface, device logistics, and the integrations connecting both to provider EHR systems. The Challenge Most remote patient monitoring programs do not fail on the monitoring. They fail on everything around it. A patient has to be enrolled, verified for insurance coverage, identified correctly in the system, onboarded, sent a device, taught to use it, and supported when the device stops working. Only then does monitoring begin. Then the data has to reach clinicians in a form they can act on, flow into the EHR, and support a billable claim. Rhythm needed four things solved together. The full lifecycle in one system. Enrollment, verification, device fulfilment, monitoring, alerting, and billing handled across separate tools means every patient is touched manually at multiple points, and the program cost per patient never comes down. Physical logistics inside a software platform. RPM is one of the few healthcare software categories with a shipping and hardware support problem attached. Devices have to reach patients, patients have to be trained, and failures have to be resolved without a clinic absorbing the support load. Alert volume that does not overwhelm clinicians. Continuous monitoring generates continuous data. Passing all of it to clinical staff produces alert fatigue, which is the failure mode that quietly ends RPM programs. Bi-directional EHR integration. One-way data push leaves clinicians reconciling two records. Real integration means monitoring data lands in the EHR and patient context flows back into the monitoring platform. Our Solution A single SaaS platform where the patient journey, the device, the monitoring data, and the reimbursement record are all connected. Enrollment and insurance verification feed onboarding. Onboarding triggers device ordering and shipping. Devices report into ongoing monitoring. Monitoring produces triaged alerts. Alerts and monitoring time support billing. The EHR stays synchronized throughout. This is the architecture behind our remote patient monitoring development work. Implementation and Approach Workflow mapping across both user groups. Patients and clinical staff use the same platform for different purposes. We mapped both journeys before building, because a system optimized only for clinicians produces patient drop-off, and one optimized only for patients produces clinical workarounds. Enrollment and verification first. Patient enrollment with insurance verification was built as the entry point, so coverage is established before device cost is incurred rather than after. Patient identification and onboarding. Identity resolution and structured onboarding, so patients are correctly matched to records and reach active monitoring rather than stalling after signup. Device logistics as a platform function. Ordering, direct-to-patient shipping, and training were built into the platform rather than handled as an external operational process, with device problem resolution workflows for the failures that inevitably follow. Triage layer between data and clinicians. Rather than route every reading to clinical staff, alerts pass through triage logic first, so what reaches a clinician is prioritized and actionable. Bi-directional EHR integration. Integration channels built to move monitoring data into provider EHR systems and pull patient context back, using the same interoperability patterns as our healthcare integration services. Billing workflow support. Monitoring activity and documentation structured to support reimbursement, with billing guidance surfaced where staff need it rather than in a separate process. Technology Stack Layer Technology Engineering rationale Backend Node.js Event-driven, non-blocking model suits continuous inbound device data and real-time alert processing Frontend AngularJS Structured data binding suits the form-heavy enrollment, verification, and clinical dashboard interfaces Database MongoDB Document model handles varied device payload structures and time-series monitoring data without rigid schema migration per device type Delivery SaaS Serves patients and clinics from one platform The stack was chosen for the ingestion pattern. RPM platforms take constant small writes from many devices, which is a different load profile from transactional clinical software. If your organization already runs a stack, we build in it. Key Features SaaS solutions for patients and clinics. One platform serving both user groups with role-appropriate interfaces. Patient enrollment and insurance verification. Coverage established at intake, before device fulfilment cost is committed. Remote patient monitoring solution. Continuous collection and processing of patient vitals and device data. Patient identification, engagement, and onboarding. Identity resolution and structured onboarding that carries patients through to active monitoring. Device ordering, direct-to-patient shipping, and training. Hardware logistics handled inside the platform, including patient training on device use. Resolution of device problems. Support workflows for device failures, so hardware issues do not land on clinic staff. Ongoing monitoring. Continuous oversight of enrolled patients rather than point-in-time measurement. Real-time triaged alerts. Alerts prioritized before reaching clinicians, protecting clinical attention. Billing expertise and guidance. Reimbursement support built into the operational workflow. Bi-directional EHR integration. Monitoring data into the EHR, patient context back out. Results and Business Impact One platform instead of a stitched-together program. Enrollment, verification, logistics, monitoring, alerting, and billing operate on shared data, which is what makes cost per monitored patient controllable as a program scales. Coverage confirmed before hardware ships. Insurance verification ahead
- 1
- 2